
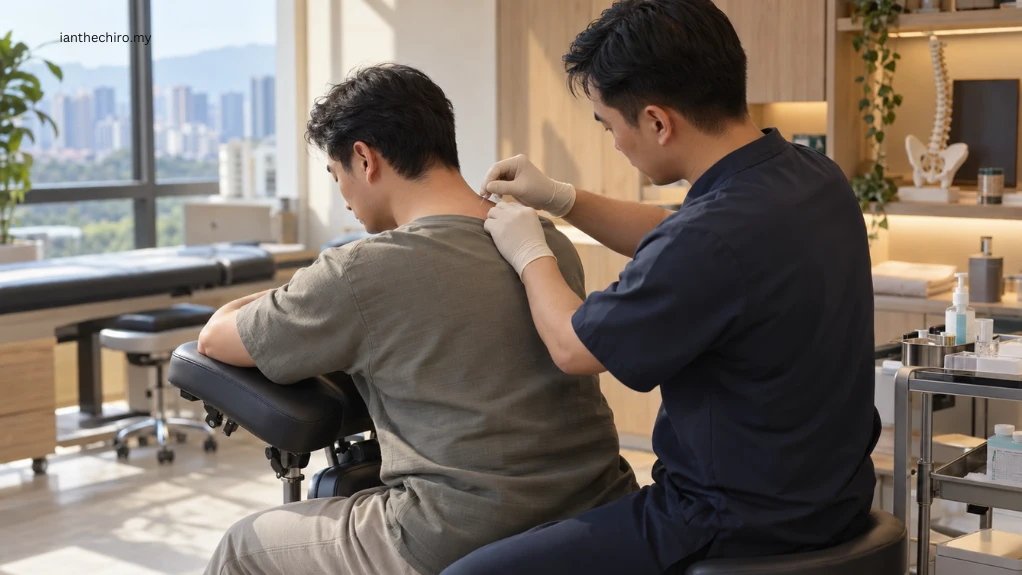
Your neck feels stiff after a week of working at a laptop. The upper shoulders are tender, turning your head feels uncomfortable, and massage seems to help only briefly. Someone suggests using needles to release the tight muscles. But is that actually the right treatment for you?
Dry needling for neck pain may offer short-term symptom relief in selected muscle-related presentations. It is not an automatic solution to every stiff neck, and relief after needling does not prove a muscle was the sole cause. Our dry needling service page explains how the technique fits into an assessment-first approach rather than being offered as a standard treatment to everyone.
Before choosing it, you need to understand what the procedure targets, what the research can support, how neck-region safety differs from other body areas, and when exercise or medical assessment is more useful. This guide helps you make that decision without promising a permanent release of a muscle knot.
Quick Answer: Does Dry Needling for Neck Pain Help?
For some people with mechanical or muscle-related neck pain, dry needling may reduce pain or tenderness over the short term. A clinician inserts thin, solid, sterile needles into selected soft tissues after examination and consent. No medicine is injected.
Its possible benefit should be weighed against other ways to manage neck pain. The evidence is more encouraging for short-term symptom improvement than for reliably lasting changes in pain, disability or neck mobility. Some people notice a difference; others have soreness or little change.
Dry needling is an option, not a prerequisite for recovery. Pain that travels with neurological changes, follows significant trauma or suggests illness requires a different assessment. And if the neck is mainly reacting to workload, sleep, sustained positions or reduced exercise capacity, treating a tender muscle alone may not produce lasting improvement.
Which Kind of Neck Pain Might Involve Sensitive Muscles?
The word “tight” describes a feeling, not a diagnosis. Several conditions can produce discomfort across the neck and shoulders. Muscle tenderness can coexist with joint sensitivity, headache patterns or symptoms arising from the neck’s nerves.
Familiar Ache Across the Upper Trapezius
An ache between the neck and the top of the shoulder, particularly after concentrated screen work, may include a muscular component. Turning the head, carrying a bag or pressing on an area of tenderness may reproduce some of the familiar discomfort.
That does not establish a specific trigger point as the cause. It does provide a reason to examine local muscle sensitivity, comfortable range of movement and how the problem responds to activity.
Local Stiffness With Tender Spots
Some people describe one or two regions of tenderness that feel like knots. A clinician may consider needling if examination suggests muscle-related sensitivity is relevant and the person wants to try the technique. But a palpable tender spot is not proof that a muscle is physically stuck or requires a needle.
Neck Pain With Headache or Arm Symptoms
Neck-related headaches can coexist with muscular tenderness. However, a new severe headache, altered vision, dizziness, unusual neurological symptoms, numbness or arm weakness changes the evaluation. A neck muscle treatment cannot be presumed to address every headache or nerve-related presentation.
Our neck pain and headaches overview explains the broader range of problems that may need assessment. Where you feel tension is only one clue; the symptoms accompanying it matter just as much.
What Does Research Actually Show for Neck Pain?
A 2025 systematic review and meta-analysis of nine randomised trials involving 540 participants with chronic mechanical neck pain reported some short-term improvements in pressure-pain sensitivity and disability measures following dry needling. Some directions of neck movement improved, while other range-of-motion outcomes did not show a significant difference.
These results suggest possible benefit, not a guaranteed response. The included trials varied in needling technique, dosage, comparators and the types of neck pain assessed. A statistical difference does not mean every patient will experience a meaningful improvement, and the review did not demonstrate dependable long-term relief.
Earlier systematic reviews also found that results vary according to the comparison treatment. Needling may outperform sham or minimal treatment in some studies, while differences against active therapies can be smaller or uncertain. It is therefore misleading to describe dry needling as proven superior to exercise, manual therapy or every other intervention.
The relevant question is whether a short-term change would help you move, sleep or participate in a broader programme. Evidence for symptom relief is not evidence that a needle repairs a disc, permanently lengthens muscle tissue or corrects spinal alignment.
Is Needling Better Than Stretching, Massage or Exercise?
Different interventions attempt different things. A gentle neck movement or strengthening programme can gradually improve tolerance for turning, carrying and sitting. Massage may offer comfort through hands-on pressure, and our dry needling versus massage guide explains how the approaches differ. Dry needling involves skin penetration and may be chosen for a more targeted short-term symptom trial when muscle sensitivity seems clinically relevant.
Those are not interchangeable techniques. If the main difficulty is sitting through a long day, a brief improvement in tenderness may help you start exercising, but it does not remove the need to manage workload and rebuild comfortable movement. Someone who prefers not to have needles can still pursue an active recovery plan.
Dry needling and acupuncture both use thin needles, but their assessment frameworks and goals may differ. Dry needling in this clinic is aimed at selected musculoskeletal findings rather than traditional meridian-based treatment. Our dry needling versus acupuncture comparison explains those distinctions without assuming one approach is always better.
Chiropractic adjustments are different again: they use manual force applied to joints, not needles inserted into muscles. Neither adjustment nor needling is a mandatory add-on to the other. The choice should be explained separately, based on examination, suitability and informed consent.
Who Might Reasonably Consider a Trial of Dry Needling?
Imagine a person who has persistent soreness at the top of one shoulder, feels guarded turning toward that side, and has a familiar tender muscle area. There are no concerning neurological or medical findings, and the person understands that the goal is symptom relief rather than a cure. This could be a reasonable situation in which to discuss a cautious needling trial.
A different person has neck discomfort mainly after several hours at a laptop, little reproducible muscle tenderness and good movement tolerance once they take a short walk. Their priority may be improving work breaks, exercise exposure and activity variety. Dry needling might add little.
Another person reports severe shooting arm pain, progressive hand weakness and sensory changes. The clinician needs to evaluate those findings before deciding whether any local soft-tissue treatment is appropriate. Needling the upper trapezius simply because it feels tight would not answer the neurological question.
The strongest reason to choose a needle is a clear, shared treatment goal after assessment, not the presence of a muscle knot on its own. A patient may also decline needling at any point and ask about alternatives.
What Happens Before Needling the Neck?
A safe appointment begins with questions about symptom onset, everyday activities, headache and arm symptoms, medical history, medication, bleeding or bruising risk, prior procedures and the person’s experience with needles. The clinician examines relevant movement, tenderness and neurological findings where indicated.
Before the procedure, you should understand why needling is being suggested, the specific region involved, expected discomfort, other options and possible adverse events. You should have an opportunity to ask questions and to stop or decline without pressure. Informed consent is especially important around the neck and upper shoulders.
The clinician should use a clean technique, appropriate positioning and sterile single-use needles. Exact targets and techniques are clinical decisions, not instructions for patients to reproduce at home. More needles, deeper insertions or a stronger twitch are not reliable measures of better care.
Our guide on whether dry needling hurts describes the possible initial prick, dull ache and brief muscle twitch in more detail. Treatment should be adjusted to the patient’s tolerance, not performed as a test of toughness.
What Might You Feel During a Neck Session?

Sensation varies. Some people report a brief prick followed by pressure or a dull muscular ache. Others notice a short twitch or a familiar referred sensation. No dramatic response is required for the treatment to count as a valid trial.
An unexpected electric sensation, intense pain, increasing distress or feeling faint should be communicated immediately. The clinician can pause, reposition, stop or choose another approach as appropriate. Patients who dislike needles should not feel obliged to endure one.
It is reasonable to ask which movements you are trying to improve. For example, if turning to reverse a car is uncomfortable, the clinician can compare that activity before and after the session. A change in the movement may be helpful feedback, but it does not prove the exact source of pain.
For people commuting through Kuala Lumpur or working long desk hours, the relevant goal is often being able to turn, look up and get through daily tasks more comfortably, not simply making a tender point less painful when pressed.
When Should Dry Needling Be Delayed or Avoided?
Not everyone is a suitable candidate on the day they attend. An active infection, an open wound near the proposed area, inability to give informed consent, a significant bleeding problem or certain recent surgical situations may make needling inappropriate. Severe needle phobia is another reason to choose a different approach.
Several circumstances call for additional discussion rather than an automatic yes or no. Tell your clinician if you take anticoagulants, bruise easily, are pregnant, have significant immune suppression, have fragile skin or use medicines that affect tissue healing. Also mention previous fainting episodes, reactions to needles or relevant medical devices.
A 2026 expert-consensus paper on dry-needling decision-making emphasised screening for contraindications and precautions, and adjusting or deferring the procedure according to the person’s risk and tolerance. It is a consensus framework rather than high-certainty proof of effectiveness. Decisions in a particular clinic also depend on professional training, scope and applicable local requirements.
Consent and risk screening are part of the treatment, not optional paperwork. If the risk is unclear, a clinician should choose a safer alternative or arrange medical advice rather than pressing ahead.
Why Does Needling Around the Neck Require Particular Care?
The neck, upper shoulder and upper-back regions contain important nerves, blood vessels and nearby structures. A qualified clinician must understand the specific anatomy and safe technique for the selected region. Patients should not try self-needling or allow an untrained person to insert needles.
Minor bruising, small amounts of bleeding and transient soreness can occur. Less common but more serious complications include infection, nerve or vascular injury, and pneumothorax, where air enters the space around a lung. The last complication is especially relevant when needling near the upper chest or back. Its possibility should be addressed in informed consent without implying that it happens routinely.
When a Post-Needling Symptom Is Not Ordinary Soreness
Chest pain, new shortness of breath, difficulty breathing or unusual worsening symptoms after needling around the upper torso require urgent medical assessment. Do not assume breathing symptoms are just a muscle twitch or normal post-treatment tenderness. Persistent significant bleeding, spreading redness, fever or new neurological deficits also need prompt attention.
Routine neck pain itself can sometimes reflect problems requiring urgent medical care, including severe headache with unusual neurological signs, significant injury, progressive limb weakness or systemic illness. These situations call for appropriate evaluation before considering a needle-based musculoskeletal treatment.
What Should You Expect Afterwards?
You may leave a session feeling a little looser, unchanged or mildly sore around the treated region. Post-needling soreness often settles over the following day or two, but individual responses vary. A little discomfort is not evidence that the treatment reached the right muscle, and an absence of soreness does not mean nothing happened.
If the upper shoulder feels tender, keep movement comfortable and avoid immediately testing it with aggressive stretching or demanding upper-body work. Ordinary gentle movements and light activity may be suitable when symptoms allow. The clinician can provide specific advice based on the site, dose and how you responded.
The more detailed article on what to expect after dry needling covers soreness, bruising, activity changes and follow-up concerns. For this neck-specific decision, the essential question is whether any temporary soreness is acceptable relative to the potential benefit and whether the procedure was appropriate in the first place.
A useful session should leave you with a clear aftercare plan and knowledge of which symptoms require help.
What If the Relief Lasts Only a Day or Two?
A short-lived improvement can still be useful if it makes sleep, movement or an exercise session more manageable. But repeatedly needling the same area without reassessing what is driving the symptoms is unlikely to be a complete management strategy.
If neck tension reliably returns after a long video meeting, consider whether varying your position, taking brief movement breaks and building comfortable neck and shoulder endurance changes the pattern. If the problem follows heavy training, load management may be more relevant. If pain returns with headaches or arm symptoms, the explanation might need to be reconsidered.
Do not equate repeated tenderness with a muscle that needs permanent release. The test of usefulness is a meaningful change in daily function, not whether the same knot can be found again.
What Are Your Options If You Prefer Not to Have Needles?
You can still work on neck pain without dry needling. Depending on your history and examination, a plan may involve gentle movement, strengthening the neck and upper back, adjusting training or desk demands, improving sleep habits, or short-term manual treatment where appropriate.
For someone whose symptoms mainly increase during laptop use, our guide to neck pain from laptop work explores position changes and activity tolerance. The answer does not have to be buying special equipment or holding the spine perfectly straight all day. A practical programme should fit the work and movement demands you actually face.
Someone with persistent pain or headache may need a different assessment or medical review. Choosing not to undergo an invasive procedure is a valid preference and should not limit access to education or exercise-based care.
Exercise and hands-on treatment are not interchangeable with needling. A plan can use one, several or none of these techniques depending on the findings. A needle is never the price of admission to a sensible neck-pain recovery plan.
How Can You Tell Whether a Needling Trial Was Worthwhile?
Before treatment, pick one or two meaningful tasks: turning to check traffic, sitting through a meeting, looking down to cook, sleeping without frequent waking, or returning to a light training session. Note the difficulty of those tasks rather than only the tenderness of one small area.
Afterwards, evaluate comfort during movement, how any post-treatment soreness settles and whether the benefit lasts long enough to help everyday activity. A small change in pressure tenderness without any improvement in your actual complaint may not justify repeating the same approach.
It may be useful to discuss what else is being addressed: neck and shoulder strength, stress and sleep, training load or sensitivity to sustained positions. If the same presentation persists despite repeated treatment attempts, reconsider the working explanation and whether referral or another management option is appropriate.
You should also feel informed and comfortable with the process. A treatment that makes you anxious, causes unacceptable side effects or conflicts with your preferences is not necessarily the right choice, even if somebody else found it useful.
Decide on Dry Needling After a Proper Neck Assessment
If you are considering dry needling because your neck or upper shoulders remain painful, the most useful first step is not choosing a muscle to needle. It is understanding which symptoms point toward a local muscular contribution, whether warning signs or precautions apply, and which outcome would make a treatment trial worthwhile.
At Ian The Chiro in Cheras, Kuala Lumpur, a chiropractic consultation begins with your history and movement assessment. When clinically appropriate, we can discuss dry needling alongside exercise advice, other conservative options or medical referral, so you can choose a sensible next step rather than automatically receiving needles.
Frequently Asked Questions About Dry Needling for Neck Pain
How many dry-needling sessions do I need for neck pain?
There is no evidence-based fixed number that suits everyone. The response can vary with the presentation, symptom duration, chosen technique and other care. Agree on a meaningful goal, reassess after a trial and avoid committing to repeated sessions solely because the muscle still feels tender.
Is dry needling for neck pain the same as an injection?
No. Dry needling generally uses a thin solid needle without injecting medication or fluid. An injection uses a different procedure and may deliver a substance. The fact that nothing is injected does not eliminate the need for sterile technique, anatomy knowledge and informed consent.
Does a muscle twitch mean the treatment is working?
Not necessarily. A local twitch can occur when a muscle is stimulated, but a strong twitch is not required for relief and is not a reliable measure of long-term success. It is more useful to compare your symptoms and meaningful daily activities after the session.
Can dry needling help a headache that starts near my neck?
Possibly in some muscle-associated presentations, but headaches have many potential causes. A new, unusually severe headache or one accompanied by concerning neurological symptoms needs medical assessment. Needling is not a substitute for evaluating migraine, nerve-related symptoms or other possible explanations.
Can I exercise after having my neck or shoulder muscles needled?
Often gentle movement is reasonable, although a treated area may be temporarily sore. If a heavy gym session, overhead work or aggressive stretching worsens symptoms, modify it for the day. Your clinician should explain the expected aftercare based on the region and response.
What if I am afraid of needles or take blood thinners?
Tell the practitioner before any procedure. Needle anxiety, a fainting history and medicines affecting bleeding change the discussion, and some circumstances make treatment unsuitable. You can decline needling and discuss non-needle options without needing to justify your preference.
